Caregiver medication list template for families
Caregiver medication list template for families to record current medicines, recent changes, pharmacy details, and questions to share at appointments.
Get the free printable caregiver medication list ↓No account required.By Rachel Moore, Founder, Sagebeam · Published August 2026 · How we research and review our guides
Part of: Care coordination for aging parents – simple system
A caregiver medication list gives relatives one current record to bring to appointments, share during handoffs, and find in an emergency. The FDA recommends keeping a list of prescription medicines, over-the-counter medicines, vitamins, and supplements; recording the name, strength, purpose, and instructions; updating it when something changes; and sharing it with caregivers and health professionals (FDA medication-list guidance).
This page is built for the family-caregiver handoff: what is current, what recently changed, when the list was last checked, and what still needs an answer. It is not meant to replace the pharmacy label, patient portal, clinic record, or a medication administration record.
This is a RECORD-AND-SHARE tool — do not change doses or schedules; confirm all medication decisions with the prescriber or pharmacist.
This guide is educational and is not medical or legal advice. Follow the instructions on the medication label and the guidance from your parent's prescriber or pharmacist.
Related resources:
- Doctor appointment checklist after a hospital stay — bring the list and mark questions before the visit.
- Doctor visit summary template for family caregivers — record any confirmed medication changes and next steps.
- Emergency medical information sheet template — point emergency staff to the detailed medication list.
- How to track an aging parent's medications and appointments — build a light routine for keeping the list current.
On this page:
- What belongs on a family caregiver medication list
- Caregiver medication list template
- Weekly medication schedule chart (checkbox grid)
- How to verify and share the list
- Tips for keeping one family version current
Jump to template: Caregiver medication list
What belongs on a family caregiver medication list
Keep the list narrow enough that someone will update it. Include:
- Current medicines: prescriptions, over-the-counter medicines, vitamins, and supplements.
- The label details: name, dose or strength, schedule, prescriber, and stated purpose.
- Pharmacy: name, location, phone number, and who usually handles refills.
- Last-verified date: when someone last compared the list with labels, the portal, or a clinician-confirmed list.
- Recent changes: what was started, stopped, or changed, plus who confirmed it and when.
- Open questions: items to ask the prescriber or pharmacist at the next appointment.
Do not guess at missing information. Write “needs confirmation” and route the question to the prescriber or pharmacist.
Caregiver medication list template (copy and adapt)
Copy this medication list for caregivers into a document or shared note. You can also print it and keep it behind your parent's emergency information sheet.
CAREGIVER MEDICATION LIST – FAMILY RECORD

Parent / person taking the medicines: ___________________________________
Date of birth: ______________________

Last verified on: ___________________
Verified against (check all that apply):
[ ] Medication bottles / labels
[ ] Pharmacy list
[ ] Patient portal or clinic list
[ ] Prescriber or pharmacist review

Family list owner: __________________________   Phone: ___________________

ALLERGIES / REACTIONS
(Copy the recorded allergy and reaction. Do not interpret.)
________________________________________________________________________
________________________________________________________________________

CURRENT PRESCRIPTION MEDICINES

1. Medicine name: ______________________________________________________
   Dose / strength exactly as listed: __________________________________
   Schedule exactly as listed: _________________________________________
   Route / form + other label instructions exactly as written: _________
   Prescriber: _________________________________________________________
   Purpose stated by care team / label: _________________________________

2. Medicine name: ______________________________________________________
   Dose / strength exactly as listed: __________________________________
   Schedule exactly as listed: _________________________________________
   Route / form + other label instructions exactly as written: _________
   Prescriber: _________________________________________________________
   Purpose stated by care team / label: _________________________________

3. Medicine name: ______________________________________________________
   Dose / strength exactly as listed: __________________________________
   Schedule exactly as listed: _________________________________________
   Route / form + other label instructions exactly as written: _________
   Prescriber: _________________________________________________________
   Purpose stated by care team / label: _________________________________

4. Medicine name: ______________________________________________________
   Dose / strength exactly as listed: __________________________________
   Schedule exactly as listed: _________________________________________
   Route / form + other label instructions exactly as written: _________
   Prescriber: _________________________________________________________
   Purpose stated by care team / label: _________________________________

5. Medicine name: ______________________________________________________
   Dose / strength exactly as listed: __________________________________
   Schedule exactly as listed: _________________________________________
   Route / form + other label instructions exactly as written: _________
   Prescriber: _________________________________________________________
   Purpose stated by care team / label: _________________________________

OVER-THE-COUNTER MEDICINES, VITAMINS, AND SUPPLEMENTS

1. Name: ______________________________ Dose / strength: ________________
   Schedule: ___________________________ Purpose: ________________________
2. Name: ______________________________ Dose / strength: ________________
   Schedule: ___________________________ Purpose: ________________________
3. Name: ______________________________ Dose / strength: ________________
   Schedule: ___________________________ Purpose: ________________________

PHARMACY

Pharmacy name / location: ______________________________________________
Phone: ________________________________
Family member who usually handles refills: ______________________________

RECENT MEDICATION CHANGES

Date: __________  Medicine: ____________________________________________
[ ] Started  [ ] Stopped  [ ] Dose changed  [ ] Schedule changed
What the prescriber or pharmacist confirmed: ____________________________
Confirmed by: __________________________  Date confirmed: _______________

Date: __________  Medicine: ____________________________________________
[ ] Started  [ ] Stopped  [ ] Dose changed  [ ] Schedule changed
What the prescriber or pharmacist confirmed: ____________________________
Confirmed by: __________________________  Date confirmed: _______________

QUESTIONS FOR THE NEXT APPOINTMENT OR PHARMACY CALL

1. ____________________________________________________________________
2. ____________________________________________________________________
3. ____________________________________________________________________

SHARING CHECK

[ ] Copy is in the caregiver binder / emergency folder
[ ] Family backup has the current version
[ ] Copy is ready for the next appointment
[ ] Old versions are marked "outdated" and stored separately or discarded

SAFETY REMINDER
Record and share only. Do not change doses or schedules. Confirm all
medication decisions with the prescriber or pharmacist.
Add more medicine rows if needed. If the list becomes hard to scan, keep the current medicines on the first page and recent changes and questions on the second.
Weekly medication schedule chart (checkbox grid)
The list above answers "what does she take?" A second question runs the actual week: "was the morning round given yet?" This weekly medication schedule chart is the companion sheet for that — the list's schedule column, unrolled into a 4-times-daily × 7-day checkbox grid a family can post on the fridge and mark as doses are given.
Copy the medicine names and time slots from the list above (which copied them from the labels), print one chart per week, and check boxes as each round happens — not from memory at night. The chart is a family coordination sheet, not a formal medication administration record: if your parent is in a care setting that requires a MAR, use the format that setting provides.
WEEKLY MEDICATION SCHEDULE CHART

Person: ____________________  Week of: __________
Copied from the medication list verified on (date): __________

Time slots (from the labels — e.g., morning / noon / evening /
bedtime; leave unused slots blank):
  Slot 1: ________  Slot 2: ________  Slot 3: ________  Slot 4: ________

MEDICINE: ______________________  Dose (from the list): __________
          Mon   Tue   Wed   Thu   Fri   Sat   Sun
  Slot 1  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 2  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 3  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 4  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]

MEDICINE: ______________________  Dose (from the list): __________
          Mon   Tue   Wed   Thu   Fri   Sat   Sun
  Slot 1  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 2  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 3  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 4  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]

MEDICINE: ______________________  Dose (from the list): __________
          Mon   Tue   Wed   Thu   Fri   Sat   Sun
  Slot 1  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 2  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 3  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]
  Slot 4  [ ]   [ ]   [ ]   [ ]   [ ]   [ ]   [ ]

  Missed or late doses (note honestly, and ask the prescriber or
  pharmacist what to do about a missed dose rather than deciding
  at home): _______________________________________________________

  Who gave each round today (initials by slot): ___________________

SAFETY REMINDER
Record only. The times and doses come from the labels via the
medication list — do not change them here. Confirm all medication
decisions with the prescriber or pharmacist.
Copy the medicine block as many times as the list needs — one block per medicine, in the same order as the master list above.
After a hospital stay, rebuild this chart from the discharge medication list — not from the old chart. Hospital stays routinely start, stop, and change medicines, and the most dangerous week for a stale schedule chart is the first week home. Walk through the reconciliation steps in how to manage new medications after a hospital stay, update the master list above from the discharge paperwork (marking anything unclear "needs confirmation" for the prescriber or pharmacist), and only then write a fresh week's chart from the updated list. Mark the old chart "outdated" the day your parent comes home.
How to verify and share the list
Pick one family member to own the list, even if several people help with care. The owner does not make medication decisions. They keep the record from splitting into several conflicting versions.
Use this short rhythm:
- Copy, do not translate. Enter the medication name, dose or strength, and schedule exactly as written on the label or confirmed by the care team.
- Mark uncertainty. If a bottle, portal, discharge list, or family note does not match, write “needs confirmation.” Ask the prescriber or pharmacist which instruction is current.
- Date every confirmed change. Record who confirmed it and when. Do not rely on an undated text message.
- Update the last-verified date. That tells the next caregiver how much confidence to place in the page.
- Share the current version. Keep it where your parent and family expect to find it, and bring it to appointments.
If your family uses Sagebeam, keep the medication list in the shared care space so everyone sees the same version. Pair it with the appointment prep brief: recent family notes become questions before the visit, and confirmed changes from the visit go back into the shared record.
Tips for keeping the medication list useful
- Keep one current family copy. A shared list can have printed copies, but only one version should be treated as current.
- Write the verification date at the top. “Current” without a date is hard to trust.
- Include nonprescription products. Over-the-counter medicines, vitamins, and supplements belong on the list too.
- Keep recent changes separate from current medicines. A stopped medicine should not look active, but the family may still need to remember when it changed.
- Bring questions, not conclusions. Write down the mismatch or concern and ask the prescriber or pharmacist to resolve it.
- Protect private information. Share the list with people involved in care and store printed or digital copies where your family has agreed they belong.
Frequently asked questions
What should a caregiver medication list include?
Include each current prescription, over-the-counter medicine, vitamin, and supplement; the name, dose or strength, schedule, prescriber, and purpose; the pharmacy and phone number; the date the list was last verified; recent starts, stops, or changes; and questions for the next appointment. Record what the label or care team says without interpreting or changing it.
How often should a family caregiver update the medication list?
Update it whenever a prescriber or pharmacist confirms a start, stop, dose change, or schedule change. Review it before appointments and write the last-verified date at the top so relatives and clinicians can quickly see how current it is.
Is this the same as a medication administration log?
No. This is a current record to share with family members, clinicians, pharmacists, and emergency staff. The list itself doesn't document doses; the weekly schedule chart on this page is the family coordination sheet for that — still not a formal MAR. Care settings that require an administration record supply their own format; use the one your care team or care setting provides.
Can a caregiver use this list to change a medication schedule?
No. Copy the medication name, dose, and schedule exactly from the label or confirmed instructions. Do not change doses or schedules; confirm all medication decisions with the prescriber or pharmacist.
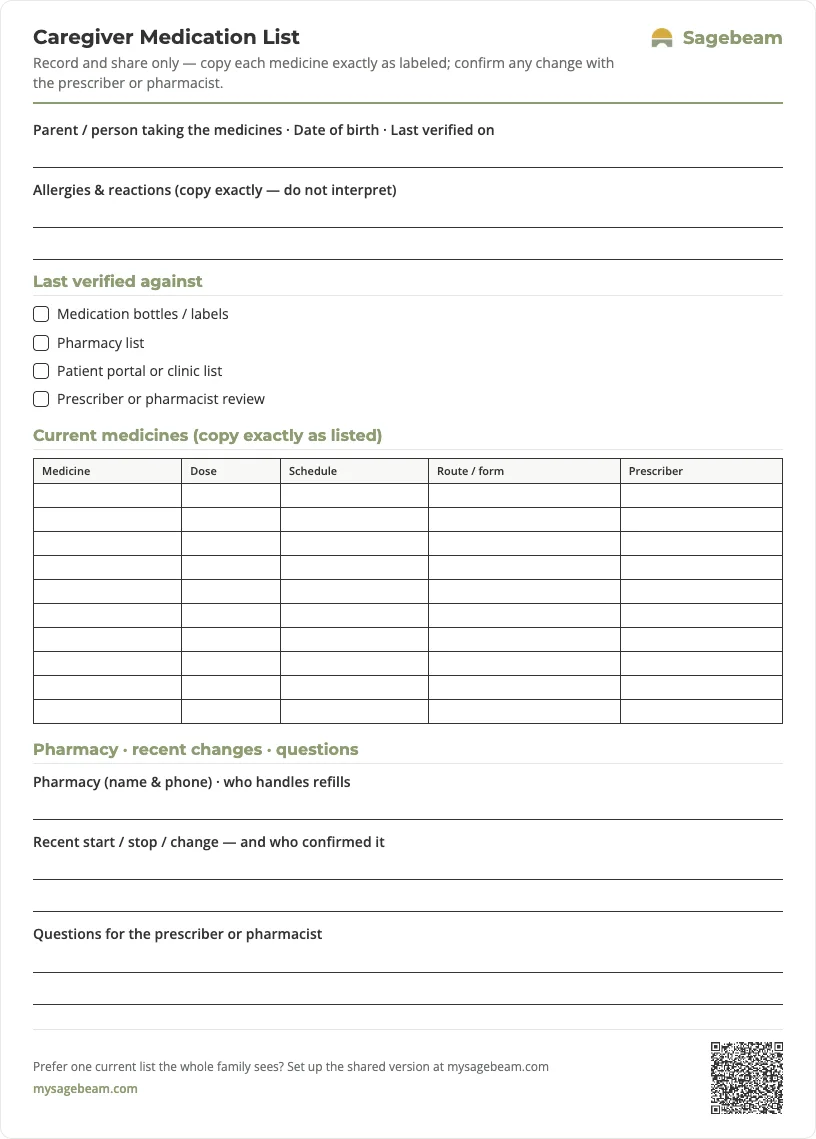
Print your caregiver medication list
A ready-to-use one-page current-medications sheet for appointments and handoffs. Copy each medicine exactly as written on the label — this is a record, not a place to change doses.
 Sagebeam
| Medicine | Dose | Schedule | Route / form | Prescriber |
|---|---|---|---|---|
- Tube feeding log sheet for families (printable G-tube and PEG record)
- Foley catheter output log and supply tracker (printable for families)
- Bowel movement and toileting log for elderly care (printable chart)
- Non-weight-bearing recovery support roster for families
You don't need more tabs. You need one place to run your parent's care.
By signing up, you agree to the Terms and Privacy Policy.